
Semaglutide research now spans more than a decade of trial data, and the pattern is consistent: durable double-digit weight loss, a 20% reduction in major cardiovascular events among high-risk patients, and meaningful glycemic control in type 2 diabetes. The tradeoffs are just as consistent. Gastrointestinal adverse events drive most discontinuations, a rodent thyroid C-cell signal keeps regulators cautious, and long-term data beyond five to six years remains thin. Everything below unpacks the trials and mechanisms behind that verdict.
TL;DR:
- Semaglutide demonstrates durable weight loss exceeding 15% on average over 68 weeks, with continuous treatment being necessary to maintain results.
- Gastrointestinal side effects, mainly nausea, cause the highest discontinuation rates, especially during dose escalation, requiring careful titration.
- Higher doses, like 7.2 mg, may increase weight loss but also raise gastrointestinal adverse events, narrowing the benefit-risk margin.
- Long-term safety beyond five to six years remains uncertain, especially regarding thyroid C-cell tumors and rare adverse conditions, demanding careful monitoring in extended use.
Table of Contents
- Semaglutide Clinical Trials: What the Pivotal Studies Found
- How Does Semaglutide Work at the Molecular Level?
- Which Semaglutide Formulations Are FDA-Approved and For What?
- What Are the Main Safety Signals in Semaglutide Trials?
- What Emerging Semaglutide Research Is Reshaping the Field?
- How Should Researchers Design Semaglutide Studies?
- What Tools Help Validate Semaglutide Research Materials?
- Pharmacogenomics and Personalized Semaglutide Response
- Immunogenicity: Does Antibody Formation Affect Semaglutide Efficacy?
- Semaglutide Drug Interactions and Conditions That Affect Pharmacology
- Where Should Semaglutide Research Priorities Go From Here?
- Where to Find Verified Semaglutide Research Materials
- Sources
Semaglutide Clinical Trials: What the Pivotal Studies Found
The clinical evidence base for semaglutide breaks into three lanes: weight management, cardiovascular risk reduction, and glycemic control. Each lane has its own pivotal program, and the effect sizes differ enough that lumping them together does a disservice to anyone trying to interpret applicability.
STEP program and durable weight loss. The Semaglutide Treatment Effect in People with Obesity (STEP) trials established the drug's headline result: sustained, double-digit percentage weight loss that holds up over extended follow-up rather than plateauing early and rebounding. The original 68-week trial reported in the New England Journal of Medicine found mean weight reductions around 15% with once-weekly semaglutide 2.4 mg, compared with a low single-digit change on placebo. That magnitude separates semaglutide from most prior anti-obesity pharmacotherapy, where 5 to 10% loss was considered a strong outcome.
Durability matters more to researchers than the headline number. Extension data from the STEP program shows that patients who continue treatment tend to maintain the bulk of their weight loss well past the primary 68-week endpoint, while those who discontinue typically regain a substantial portion within a year. That regain pattern has become one of the more cited arguments for treating obesity as a chronic condition requiring continuous therapy rather than a course of treatment with a defined endpoint.
SELECT and cardiovascular outcomes. The SELECT trial changed how the cardiology community talks about GLP-1 receptor agonists. In patients with preexisting cardiovascular disease and overweight or obesity but without diabetes, once-weekly semaglutide 2.4 mg reduced the composite endpoint of cardiovascular death, nonfatal myocardial infarction, or nonfatal stroke by a significant margin versus placebo, with a hazard ratio of 0.80 over a mean follow-up of roughly 39.8 months, as reported in the SELECT trial published in NEJM.
Statistic callout: SELECT enrolled patients specifically for cardiovascular risk, not diabetes status. Primary endpoint event rates were 6.5% in the semaglutide group versus 8.0% on placebo, a gap wide enough to shift how clinicians think about GLP-1 agents outside diabetes and weight-management indications entirely.
That trial protocol and its full statistical methodology are searchable under Clinicaltrials (NCT03574597), which is worth pulling directly if you're designing a follow-up study or a subgroup analysis.
SUSTAIN and PIONEER: the diabetes evidence. Before STEP and SELECT, the SUSTAIN program (injectable) and PIONEER program (oral) established semaglutide's glycemic profile in type 2 diabetes. Across these trials, semaglutide consistently produced HbA1c reductions in the range of 1.0 to 1.8 percentage points depending on dose and background therapy, generally outperforming comparator GLP-1 agents and basal insulin regimens on both glycemic control and body weight. Cardiovascular safety in this population was reassuring rather than dramatically protective, a distinction worth flagging because SELECT's stronger cardiovascular signal came from a nondiabetic, high-risk population, not from the diabetes trials themselves.
Higher-dose STEP UP findings. The STEP UP trial tested a 7.2 mg maintenance dose against the standard 2.4 mg regimen, motivated by dose-response data suggesting more weight loss might be achievable at the cost of tolerability. Early results point toward incremental weight-loss gains at the higher dose, but with a corresponding increase in gastrointestinal adverse events and discontinuation. This is the trial researchers should watch closely if they're modeling dose-response curves or advising on off-label dose escalation.
BARI-STEP and adjunctive use after bariatric surgery. One of the more clinically useful recent findings involves patients with suboptimal weight loss following bariatric surgery, a population that historically has limited pharmacologic options. The BARI-STEP trial published in Nature Medicine found that semaglutide 2.4 mg produced a mean 18.0% weight loss at 68 weeks, compared with a 0.4% weight gain on placebo, an adjusted treatment difference of 19.18 percentage points. Safety in this post-surgical population tracked closely with the established GI-adverse-event profile seen elsewhere.
Key trial takeaways for researchers evaluating applicability:
- STEP program: a sustained double-digit mean weight loss at 68 weeks in treatment-naive patients with obesity, durable with continued therapy.
- SELECT: 20% relative risk reduction (HR 0.80) for major cardiovascular events over ~39.8 months in a nondiabetic, high-risk cardiovascular population.
- SUSTAIN/PIONEER: HbA1c reductions of 1.0 to 1.8 points in type 2 diabetes, with generally favorable weight and safety comparisons to other glucose-lowering agents.
- STEP UP: incremental weight-loss benefit at 7.2 mg but a clear tolerability trade-off.
- BARI-STEP: 19.18 percentage-point adjusted weight-loss advantage over placebo in post-bariatric patients with suboptimal initial response.
For a deeper walkthrough of the STEP program's design choices and how they inform practical program planning, USAPeptide's guide to semaglutide weight loss support and program design covers the trial-level evidence in more operational detail.
How Does Semaglutide Work at the Molecular Level?
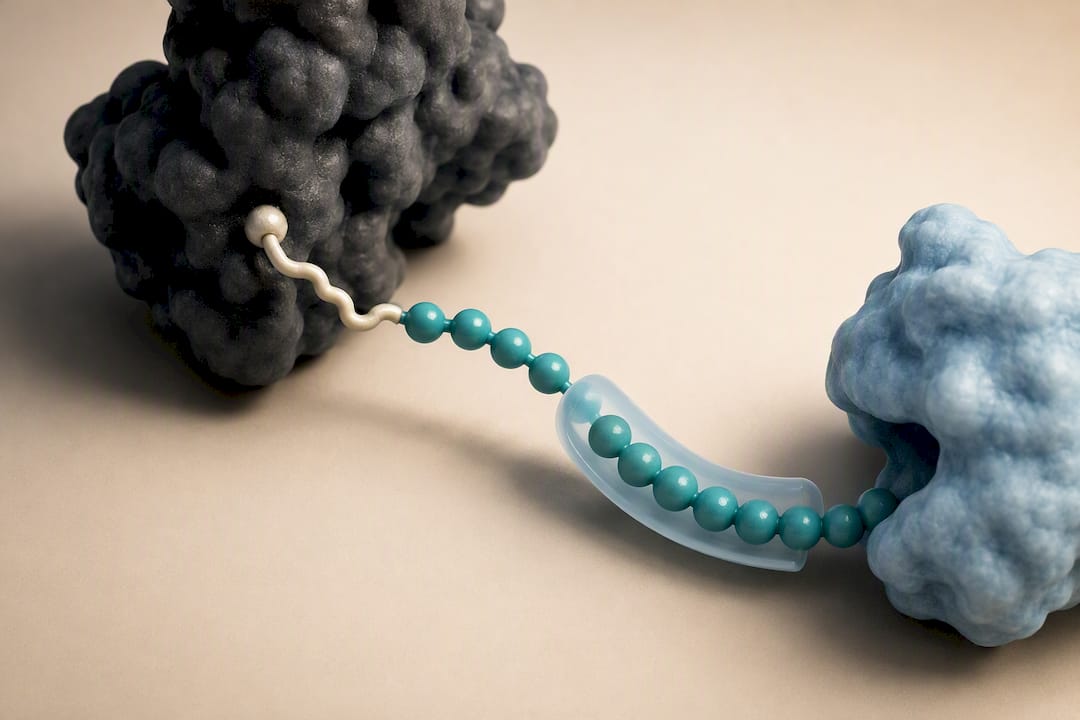
Semaglutide's clinical profile traces directly to two structural modifications made to the native human GLP-1 peptide, and understanding them explains almost everything about its dosing schedule, its exposure-driven effects, and even some of its side effects.
The first modification is acylation at the lysine residue at position 26, which attaches a fatty acid side chain that binds reversibly to serum albumin. This albumin binding does two things: it protects the peptide from rapid renal clearance and it creates a circulating reservoir that releases free drug slowly. The second modification is an amino acid substitution, replacing alanine with aminoisobutyric acid (Aib) at position 8, which blocks the peptide from being cleaved by dipeptidyl peptidase-4 (DPP-4), the enzyme responsible for degrading native GLP-1 within minutes. Combined, these changes extend semaglutide's half-life to roughly one week, which is what allows once-weekly subcutaneous dosing instead of the multiple daily injections earlier GLP-1 agents required.
Pro Tip: If you're modeling exposure-response relationships, remember that semaglutide's steady-state plasma concentration takes about four to five weeks to reach with standard titration. Any pharmacodynamic endpoint measured before that window reflects a partial exposure state, not the drug's full pharmacologic effect.
At the receptor level, semaglutide is a selective GLP-1 receptor agonist, and that single receptor mediates a surprisingly wide range of downstream effects relevant to this drug's clinical footprint:
- Appetite suppression through central GLP-1 receptors in the hypothalamus and brain stem, slowing gastric emptying and increasing satiety signaling.
- Glucose-dependent insulin secretion from pancreatic beta cells, which explains why hypoglycemia risk stays low compared with insulin or sulfonylureas.
- Direct vascular and cardiomyocyte effects that current mechanistic research increasingly treats as separate from, not purely downstream of, weight loss.
- Modulation of inflammatory signaling, evidenced by the CRP reductions seen in cardiovascular and heart-failure trials.
The oral formulation adds a pharmacological wrinkle worth understanding on its own terms. Peptides are normally destroyed by stomach acid and pepsin before they can be absorbed, which is why GLP-1 agents were injectable for years. Oral semaglutide solves this with SNAC (sodium N-[8-(2-hydroxybenzoyl)amino]capsulate), a coformulated absorption enhancer that transiently raises local gastric pH and protects the peptide from enzymatic breakdown long enough for it to cross the gastric epithelium. The resulting oral bioavailability is low, generally under 1%, but it's consistent enough to produce clinically meaningful systemic exposure when the tablet is taken correctly, meaning fasted, with a small amount of water, and no food or other medication for 30 minutes afterward. That fragile absorption window is also why oral dosing requirements are stricter and less forgiving than injectable regimens. USAPeptide's semaglutide molecular dossier breaks down the acylation and Aib substitution chemistry in more structural detail for researchers building comparative pharmacology models, and the tirzepatide dossier is a useful comparison point for anyone contrasting single versus dual-receptor agonist.
Which Semaglutide Formulations Are FDA-Approved and For What?
Three branded formulations carry distinct FDA indications, and conflating them is one of the more common errors in secondary literature and casual research summaries.
Wegovy® is approved for chronic weight management in adults and certain adolescents with obesity, or overweight with at least one weight-related comorbidity, and is also approved to reduce cardiovascular risk in adults with established cardiovascular disease and overweight or obesity. The maintenance dose is 2.4 mg subcutaneously once weekly, reached through a stepwise titration schedule that typically starts at 0.25 mg and escalates over roughly 16 weeks to minimize gastrointestinal intolerance.
Ozempic® is approved for glycemic control in type 2 diabetes and, at the 2.4 mg dose, carries a cardiovascular risk reduction indication in adults with diabetes and established cardiovascular disease. Maintenance doses in diabetes trials commonly run at 0.5, 1.0, or 2.0 mg weekly, with the higher 2.4 mg dose reserved for patients who need additional glycemic or cardiovascular benefit.
Rybelsus® is the oral formulation, approved for glycemic control in type 2 diabetes, with typical doses of 7 mg or 14 mg once daily following a lower starting dose during titration.
The label distinctions matter for anyone interpreting trial outcomes or advising off-label use:
- Wegovy carries the only FDA-approved chronic weight-management indication among the three brands.
- Only Ozempic and Wegovy carry cardiovascular risk-reduction language, and each is scoped to a different underlying population (diabetes plus cardiovascular disease for Ozempic; overweight/obesity plus cardiovascular disease for Wegovy).
- Rybelsus is the only oral option, with bioavailability constraints that make it pharmacokinetically distinct from the injectable formulations despite sharing the same active peptide.
- Titration schedules across all three formulations exist specifically to blunt gastrointestinal adverse events, and abbreviated titration is one of the more common protocol deviations in real-world and off-label use.
For researchers designing comparative-effectiveness studies, the label differences aren't just administrative. STeP trial dosing and SELECT trial dosing both used the 2.4 mg subcutaneous regimen, so any generalization to Ozempic's lower diabetes-oriented doses requires caution about extrapolating effect sizes across formulations that were never head-to-head tested against each other at matched exposure.
What Are the Main Safety Signals in Semaglutide Trials?
Gastrointestinal adverse events dominate the semaglutide safety profile, and they're the single biggest driver of trial discontinuation across every major program. The StatPearls clinical review of semaglutide notes nausea rates around 20% in trial populations, with vomiting, diarrhea, and constipation following at lower but still notable frequencies. These effects cluster heavily around dose escalation periods, which is exactly why titration schedules exist and why abbreviated titration in real-world prescribing tends to produce worse tolerability than trial protocols achieved.
Statistic callout: In SELECT, 16.6% of patients on semaglutide discontinued due to adverse events, compared with 8.2% on placebo, roughly double the discontinuation rate, and gastrointestinal disorders accounted for the largest share of that gap.
Serious adverse events tell a more reassuring story than the discontinuation numbers might suggest at first glance. Across the major trials, overall serious adverse event rates have generally run comparable between semaglutide and placebo arms, meaning the drug's tolerability problem is real but mostly limited to non-life-threatening GI symptoms rather than a broad excess of severe complications.
Three specific safety signals deserve individual attention from researchers designing monitoring protocols:
- Gallbladder disease. Cholelithiasis and cholecystitis occur at modestly higher rates in semaglutide-treated patients, plausibly related to rapid weight loss itself rather than a direct pharmacologic effect on biliary physiology.
- Pancreatitis. Signals exist across the GLP-1 receptor agonist class, though absolute incidence remains low and causality versus baseline risk in obese and diabetic populations remains difficult to fully disentangle in trial data.
- Rodent thyroid C-cell tumors. Preclinical rodent studies showed dose-dependent thyroid C-cell tumors, which is why semaglutide carries a boxed warning and is contraindicated in patients with a personal or family history of medullary thyroid carcinoma or Multiple Endocrine Neoplasia syndrome type 2. Whether this rodent signal translates to human risk remains unresolved. Human thyroid cancer incidence in long-term surveillance has not shown a clear causal signal, but rodents express thyroid C-cell GLP-1 receptors at much higher density than humans, and this species-difference argument is one researchers should present with appropriate caveats rather than dismiss outright.
The clearest evidence gap sits beyond the five- to six-year horizon most pivotal trials cover. Extension studies and postmarketing surveillance provide reassurance but not certainty about decade-scale safety, particularly for populations without preexisting cardiovascular disease who might use semaglutide chronically for weight management alone. Any monitoring protocol for a new semaglutide study should include baseline and periodic gallbladder ultrasound in high-risk patients, screening for personal or family thyroid cancer history before enrollment, and structured GI symptom tracking through at least the full titration period.
What Emerging Semaglutide Research Is Reshaping the Field?
The most consequential shift in current semaglutide research is conceptual: the field is increasingly treating this molecule as a pleiotropic cardiometabolic agent rather than a weight-loss drug with secondary cardiovascular benefits. That reframing comes directly from data suggesting cardioprotection doesn't scale cleanly with pounds lost.
Recent Nature-affiliated analysis of exposure-driven cardioprotective effects argues that cardiovascular benefit correlates with cumulative drug exposure independent of the magnitude of weight loss achieved, which has pushed researchers toward investigating direct semaglutide effects on cardiomyocytes and vascular endothelium rather than assuming weight loss is the sole mediating pathway. This matters enormously for trial design going forward. If cardioprotection is partly exposure-driven rather than purely weight-mediated, then patients who lose relatively little weight but maintain consistent dosing might still derive meaningful cardiovascular benefit, a hypothesis that current secondary analyses are actively testing.
Higher-dose regimens. The 7.2 mg dose tested in STEP UP represents the field's attempt to find where the efficacy curve plateaus against the tolerability curve. Early signals suggest additional weight loss at the higher dose comes with a proportionally larger GI adverse event burden, meaning the incremental benefit-to-risk ratio narrows rather than improves as dose increases. Where the true clinical ceiling sits remains an open question that will likely require several more years of comparative dosing data to resolve.
Heart failure with preserved ejection fraction. One of the more functionally meaningful recent findings comes from a trial in patients with HFpEF and obesity, where semaglutide 2.4 mg improved Kansas City Cardiomyopathy Questionnaire (KCCQ) scores by a mean difference of 7.8 points over placebo and reduced C-reactive protein by roughly 43.5% at 52 weeks, according to the NEJM HFpEF and obesity trial. That CRP reduction, well beyond what weight loss alone typically produces, is one of the stronger pieces of evidence supporting a direct anti-inflammatory mechanism rather than a purely mechanical, weight-mediated improvement in cardiac function.
Aging biology and pleiotropic hypotheses. Preliminary interest in semaglutide's potential relevance to aging biology, inflammation, and even neurodegeneration is growing, but researchers should treat this area as genuinely speculative. Most of the supporting evidence comes from mechanistic plausibility and secondary endpoint analyses rather than trials designed to test aging-related outcomes directly. It's a legitimate area for hypothesis generation, not yet a basis for clinical claims.
Open questions worth prioritizing in the next wave of trials:
- Whether cardioprotective effects hold independent of weight loss across broader, lower-risk populations than SELECT enrolled.
- Where the true dose-response ceiling sits between 2.4 mg and 7.2 mg once tolerability is weighted against incremental efficacy.
- How durable HFpEF functional improvements remain beyond the 52-week window already studied.
- Whether anti-inflammatory effects (CRP reduction) predict downstream outcomes independently of weight or glycemic changes.
USAPeptide's peptide research news coverage tracks trial updates as they publish, including follow-on analyses from BARI-STEP and the HFpEF program, for researchers who want ongoing visibility into this fast-moving evidence base.
How Should Researchers Design Semaglutide Studies?
Designing a rigorous semaglutide study or observational analysis means anticipating the same issues that have complicated interpretation of the pivotal trials themselves. A few practical priorities make the difference between a clean dataset and one that's difficult to analyze honestly.
- Choose endpoints that separate mechanism from outcome. Pair a hard clinical endpoint (weight change, HbA1c, MACE) with a biomarker panel (CRP, lipid profile, and where relevant NT-proBNP for cardiac studies) so mechanistic hypotheses can be tested alongside the primary outcome rather than inferred after the fact.
- Capture titration and discontinuation as first-class data, not noise. Exposure to semaglutide is not binary; a patient who discontinued at week 20 after reaching only 1.0 mg had a fundamentally different exposure than one who completed titration to 2.4 mg. Build your estimand around treatment-policy or on-treatment exposure explicitly, and specify which one before unblinding.
- Build a safety monitoring checklist into the consent process. Baseline thyroid cancer family history screening, gallbladder symptom baseline, and GI tolerability thresholds for dose-hold decisions should all be specified prospectively, not handled ad hoc.
- Plan your missing-data strategy before enrollment closes. GI-driven dropout is nonrandom, correlated with both drug exposure and the outcome you're measuring, which makes naive complete-case analysis a real bias risk. Multiple imputation or a formal treatment-policy estimand handles this more defensibly than post hoc sensitivity analysis.
Pro Tip: Specify your estimand strategy in the protocol before you see any outcome data. Reviewers increasingly expect a clear statement of whether you're measuring the treatment-policy effect (intention-to-treat regardless of discontinuation) or the while-on-treatment effect, because semaglutide's discontinuation-driven missingness pattern makes the two answers meaningfully different.
What Tools Help Validate Semaglutide Research Materials?
Rigorous semaglutide research, whether preclinical or translational, depends on knowing exactly what's in the vial or tablet you're studying. USAPeptide.info's peptide dossier for semaglutide lays out the molecular structure, the acylation and Aib modification chemistry, and half-life pharmacokinetics in a single reference, useful when you need to cite mechanistic detail without re-deriving it from primary sources each time.
Two additional tools address a more practical problem: verifying material quality before it enters a study. USAPeptide's COA grading tool evaluates Certificates of Analysis for legitimacy markers, flagging inconsistencies that can indicate a supplier is not testing to the purity it claims. A dosage calculator supports researchers translating trial-derived dosing schedules into bench-appropriate concentrations for preclinical or comparative work. Neither tool replaces independent HPLC verification, but both reduce the chance that a study's conclusions get undermined by unverified starting material, a failure mode that's more common in peptide research than most published papers acknowledge.

Pharmacogenomics and Personalized Semaglutide Response
Individual response to semaglutide varies substantially, and pharmacogenomic research is beginning to probe why some patients lose 20% of body weight while others plateau closer to 5%. GLP-1 receptor gene polymorphisms are the most obvious candidate mechanism, since variation in receptor density or binding affinity would plausibly alter both efficacy and tolerability, but large-scale genotype-stratified trial data specific to semaglutide remains sparse.
Beyond genetics, baseline metabolic phenotype appears to matter more than genotype in current evidence. Patients with higher baseline insulin resistance or specific gut hormone profiles tend to show different weight-loss trajectories on GLP-1 therapy, though this observation comes mostly from smaller mechanistic substudies rather than the pivotal trials themselves, which weren't designed to stratify by these markers. Body composition analysis, specifically the ratio of fat mass to lean mass lost, also varies between patients in ways that aren't yet predictable from baseline characteristics alone.
For researchers, the practical implication is that semaglutide response heterogeneity is real and clinically relevant, but the field lacks a validated biomarker or genetic panel that reliably predicts who will be a high responder before treatment starts. Prospective studies that collect baseline genotype, gut hormone panels, and body composition data alongside standard efficacy endpoints would meaningfully advance this question, and it remains one of the more underexplored areas relative to how much clinical variability it likely explains.
Immunogenicity: Does Antibody Formation Affect Semaglutide Efficacy?
Immunogenicity is a smaller concern with semaglutide than it was with earlier, less human-homologous GLP-1 agents, largely because semaglutide's structure closely mirrors native human GLP-1 aside from the two targeted modifications. Anti-drug antibody formation has been detected in a minority of trial participants across the semaglutide clinical program, but these antibodies have generally not been associated with meaningful loss of glycemic or weight-loss efficacy in the populations studied.
That reassurance comes with a caveat researchers should keep in mind: antibody surveillance in the pivotal trials wasn't the primary focus, and long-term, real-world immunogenicity data at scale is still accumulating. Cross-reactivity with native GLP-1 is a theoretical concern given the structural similarity, though no clear signal of clinically significant cross-reactivity has emerged in published safety reporting to date.
For translational researchers, this makes immunogenicity monitoring a low-priority but not zero-priority element of long-duration studies, particularly in cohorts using semaglutide for extended periods beyond the one- to two-year windows most pivotal trials covered. Any study running past that horizon should still include periodic anti-drug antibody assessment as a secondary safety measure, if only to build the longitudinal dataset the field currently lacks.
Semaglutide Drug Interactions and Conditions That Affect Pharmacology
Semaglutide's most clinically relevant pharmacological interaction isn't a direct drug-drug metabolic interaction but a consequence of its mechanism: delayed gastric emptying can alter the absorption kinetics of concurrently administered oral medications, particularly those with narrow therapeutic windows. Oral contraceptives, certain oral antibiotics, and levothyroxine are the drugs most often flagged for monitoring when co-prescribed with semaglutide, since delayed gastric transit can shift peak plasma concentration timing even when total absorption is ultimately similar.
Insulin and sulfonylureas require particular attention in diabetic patients, since combining them with semaglutide increases hypoglycemia risk beyond what either agent alone produces. This interaction is dose- and titration-dependent, and most protocols call for proactive sulfonylurea or insulin dose reduction when initiating semaglutide rather than waiting for a hypoglycemic event to prompt adjustment.
Renal and hepatic impairment don't require semaglutide dose adjustment based on current labeling, since the drug is cleared primarily through proteolytic degradation rather than renal or hepatic pathways, an important distinction from many small-molecule diabetes and weight-management drugs. That said, severe GI adverse events can indirectly stress renal function through volume depletion, so researchers studying semaglutide in populations with borderline renal reserve should track hydration status and renal function markers as a precaution rather than assume the drug's clearance pathway makes this a nonissue.
Where Should Semaglutide Research Priorities Go From Here?
The honest answer is that the field has over-invested in weight-loss magnitude and under-invested in mechanism and long-term safety. STEP and SELECT together generated an enormous evidence base for efficacy, but the exposure-independent cardioprotection hypothesis coming out of recent mechanistic analyses deserves more resources than it's currently getting, because it could reshape how the drug is dosed and monitored if confirmed.
Real-world effectiveness data matters just as much as pivotal trial data at this point, arguably more. Trial populations are selected, adherent, and closely monitored in ways that real-world patients often aren't. The gap between trial discontinuation rates and real-world persistence is likely wider than published literature currently reflects, and closing that gap should be a research priority, not an afterthought left to postmarketing surveillance alone.
On off-label use, we think the ethical line is clearer than the current discourse suggests: researchers and clinicians have an obligation to distinguish between prescribing within approved indications with appropriate monitoring and using semaglutide as a lifestyle drug outside any structured safety framework. The rodent thyroid signal and the still-thin decade-scale safety data mean unmonitored, indefinite use carries real unknowns, even if the known risks so far look manageable within trial-length windows.
We'd rather see the next wave of research dollars go toward mechanistic cardiac and renal studies and toward pharmacogenomic stratification than toward another weight-loss percentage headline. Researchers who want to run that kind of rigorous work should use verified materials and the tools built to support careful methodology.
— USAPeptide Team
Where to Find Verified Semaglutide Research Materials
The Peptriva Research Peptide Resource Center gives qualified researchers a single point of access to ISO 17025-accredited compound sourcing, detailed Certificates of Analysis, and same-day shipping. This matters when a study timeline depends on not waiting three weeks for a reorder.
Beyond sourcing, the COA grading tool lets you check a supplier's Certificate of Analysis for legitimacy markers before you commit a study budget to a batch, and the dosage calculator translates trial-derived regimens into bench-appropriate concentrations without manual unit conversion errors. If you're planning a comparative pharmacology study and want to see how semaglutide's single-receptor mechanism stacks up against dual-agonist approaches, the site's peptide dossiers cover that comparative context directly. Visit the Peptriva Research Peptide Resource Center to review current compound availability and start sourcing verified material for your next study.
Sources
For direct access to primary trial data: the SELECT cardiovascular outcomes trial and its registry entry (NCT03574597), the original STEP weight-management trial, the HFpEF and obesity trial, and the BARI-STEP post-bariatric adjunct trial. For pharmacology and safety review, StatPearls' semaglutide summary remains a solid single-reference starting point, and for context on brand-versus-generic comparisons, RankOfSupplements' barbering-versus-Ozempic analysis covers common label-indication confusion worth understanding before citing dosing comparisons secondhand.
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
- Once‑weekly semaglutide in adults with overweight or obesity (NEJM, 2021)
- Semaglutide — StatPearls (NCBI Bookshelf, 2024)